
London's Gulf inbound: the one Western market where the story is real
Most "attract international patients" pitches to Western clinics quietly describe a market that barely exists. London is the exception. More than 100,000 overseas residents are treated in London every year, and the self-pay core of that market sits in and around the Harley Street Medical Area — over 2,000 practitioners and clinics within a few streets.
The Gulf segment is the most established part of it. Several GCC governments fund treatment abroad for their citizens when it is unavailable at home — in some cases covering family accommodation for the duration — and private Gulf demand travels alongside it. This is institutionalised, not anecdotal: Harley Street clinics have jointly staged roadshows in the GCC to promote London medicine. When competitors are flying to the Gulf together to market, two things are true — the demand is real, and the marketing budgets already exist.
That second point matters if you run a smaller clinic or an independent consultant practice. The large private hospitals have international offices. The independents mostly don't — which is exactly the gap a visibility-based approach fits: you don't need a Dubai office to be the answer a researcher finds.
Where the decision actually happens — and a straight answer about language
Gulf patients do not walk in off Harley Street. Whether the case is government-sponsored or privately funded, someone researches it first — the patient, a family member, an office managing the case. They compare consultants, check credentials, read clinic pages, and increasingly put the question directly to AI assistants: which London clinic for this procedure, what does self-pay cost, who are the named specialists. A substantial part of that research layer runs through English-language search and English-language clinic content — and the clinics that surface there with clear self-pay information are the ones that make the shortlist.
Now the straight answer: we do not produce Arabic-language content. Our in-house production lines are English, Chinese (Traditional and Simplified), Japanese, and Spanish. Some agencies in this market sell Arabic capability; if native Arabic content is the centre of your strategy, weigh that honestly — we will say the same in the audit. What we build is the layer underneath any language strategy: English-first international self-pay visibility — the rankings, AI citations, and evidence-rich clinic content through which London shortlists are actually assembled — operated at a depth of 7,700+ pages and measured daily across four AI engines.
We would rather lose a pitch on that sentence than win an engagement on a claim we can't deliver. The same honesty applies to our numbers: every figure on this page carries its calculation basis.
What international self-pay visibility looks like for a London clinic
The asset base we build and fund for a London engagement:
Self-pay answer pages
- Procedure-level pages with transparent self-pay pricing structure, consultant credentials, and what-to-expect detail — the content researchers and AI engines actually cite
- Structured data and sources on every page — built to be quoted, not just ranked
- No promised outcomes, no promised rankings — evidence-rich and standards-aware
AI-citation coverage
- Daily measurement of where your clinic appears when ChatGPT, Gemini, Perplexity, and Google's AI Overviews are asked to shortlist London clinics
- The audit shows your current position across all four engines before anything is signed
- Domestic self-pay researchers — including patients moving around NHS waiting lists — are reached by the same coverage
Compliance-first production
- Produced with GMC and ASA/CAP advertising standards in mind — because the professional responsibility for what is published under your name stays with you and cannot be delegated
- You review and approve before anything goes live
- Multilingual upside where it fits: Chinese, Japanese, and Spanish lines for London's other international self-pay audiences
The sequencing follows the market: for a London clinic the international self-pay line often leads, while domestic self-pay growth thickens the base underneath — the reverse of how we sequence US engagements. One engine, both audiences; the domain authority and citation history compound in both directions. For the category-level view of how this differs from brokers and retainer agencies, see our international patient marketing agency guide and the broader playbook on attracting international patients. Clinics needing a full inquiry-handling layer can pair this with international patient department outsourcing.
What does this cost a London clinic?
Typical healthcare marketing retainers run £2,500–6,500 a month ($3,000–8,000) regardless of results. We priced against that structure. $0 upfront — our fee is 20% of revenue from the patient lines you assign to us, CRM-verified, with no per-patient counting. Content production, domains, hosting, rank and AI-citation tracking are funded by us; we charge nothing until revenue materialises in your CRM.
The exact base is designed around your practice during the free audit, before anything is signed — which lines you assign (international self-pay, domestic self-pay, or both), what counts as new revenue, and what is excluded automatically: existing patients, channels you run yourself, and patient lines we don't manage. The fee applies to a revenue pool, never to individual patients — we never count, steer, or broker anyone, which keeps the model cleanly on the marketing-services side of the line your professional guidance cares about. Settlement is one monthly CRM export; invoicing is in GBP to a UK-domestic receiving account, with reverse-charge VAT treatment as a non-resident supplier.
Four structural terms always travel with the 20%: $0 upfront · non-exclusive · cancel anytime · monthly CRM settlement. Keep your current agency, run your own campaigns, and have your solicitor review the agreement — we expect it. The model is documented end to end on our performance-based healthcare marketing page.
| Term | How it works |
|---|---|
| Rate | 20% flat — five new patients or five hundred, the rate never moves |
| Base | Collected revenue from the patient lines you assign — designed with you during the free audit |
| Verification | Your CRM — one monthly export, no per-patient counting, no receipts |
| Upfront cost | $0 — no retainer, no setup fee |
| Exclusivity | None — keep your current agency, run your own ads |
| Cancellation | Anytime — no lock-in, no termination fee |
Why does "proven in Seoul" matter on Harley Street?
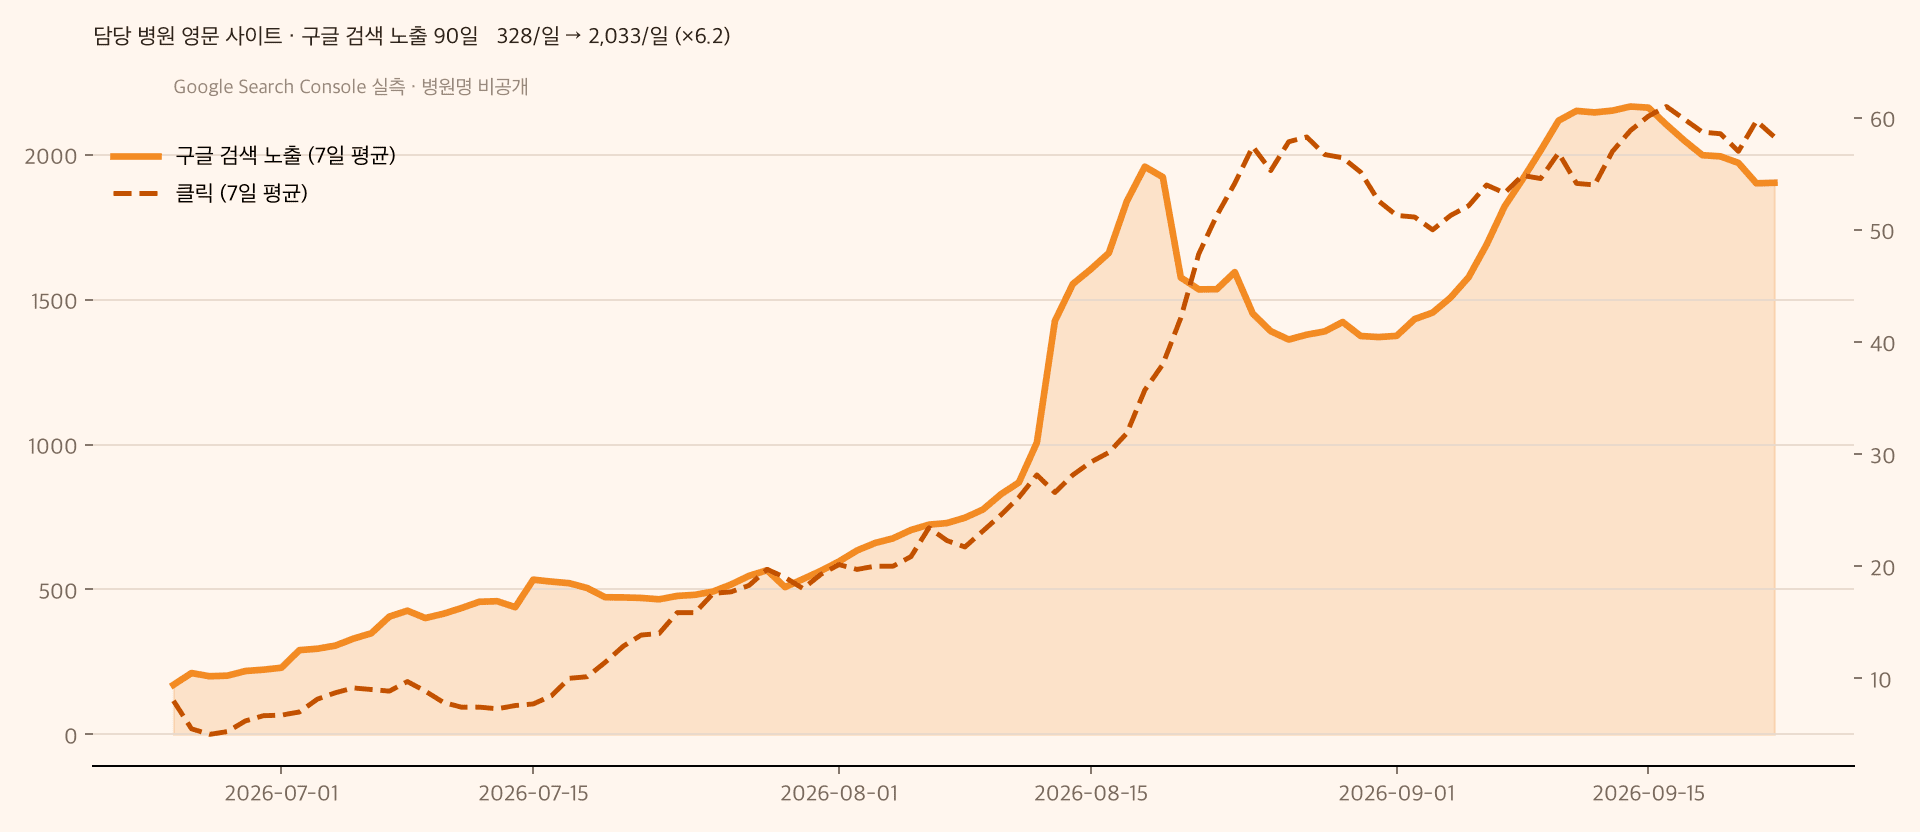
Seoul is the world's most competitive medical tourism market — over two million international patients a year, fought over in five languages at once. It is, in effect, a hundred Harley Streets stacked into one city. Ranking there, and being cited by AI there, is the credential we bring to London. Two documented cases, both dermatology clinics, both measured the same way:
What should you ask before signing with anyone?
Whether you talk to us or another vendor, five questions separate substance from a deck. First: what languages do you actually produce in-house — and can they show operated pages, not a partner brochure? (Our answer is above, including the one we don't.) Second: show me a cited answer — ask to see, live on the call, a page they built being cited by an AI engine for a clinic-selection query. Third: what do I pay for — brokered patients, billable hours, or revenue verified in my own CRM?
Fourth: who owns the assets when you part ways — the pages, the coverage, the domain authority? Fifth: who carries the compliance risk — under GMC guidance it is you, so the content must be built to that standard from the first draft, with your approval before anything goes live.
Our answers are on this page. The free AI-visibility audit exists so you can check them against your own market: where your clinic appears today when patients — in London or researching from the Gulf — ask Google, ChatGPT, and Gemini. Free, no obligation.
'/%3E%3C/svg%3E)